

Hepatitis C treatment has changed more completely than almost anything else in infectious disease. What was once a long course of injections with difficult side effects and uncertain results is now, for most people, a short course of daily tablets.
Many people diagnosed today are working from what they heard about treatment years ago. That picture is out of date, and the gap between it and current practice is wide enough to be worth closing.
Why screening matters more than symptoms
Chronic hepatitis C often produces no symptoms at all for years. When symptoms do appear they are vague: fatigue, aching joints, poor appetite. By the time the liver gives clearer signals, damage may already have accumulated.
That is the argument for testing rather than waiting. Screening is generally recommended at least once for all adults, in pregnancy, and repeatedly for anyone with ongoing risk factors.
Testing happens in two steps. An antibody test shows whether you have ever been exposed. If it is positive, a second test looks for the virus itself, because a proportion of people clear hepatitis C without treatment and remain antibody positive afterwards.
How hepatitis C is passed on
Hepatitis C is a bloodborne virus. It is transmitted when blood from an infected person enters the bloodstream of someone else, which in practice means shared injecting equipment, needlestick injuries, and unsterile tattooing or medical procedures.
Transfusions and transplants were a significant route before donated blood was routinely screened, which is why people who received blood products decades ago are often advised to be tested even with no other risk factor.
Sexual transmission is possible but uncommon in heterosexual couples, and the risk is higher where there is HIV coinfection or anything that causes bleeding. Transmission from mother to baby occurs in a minority of pregnancies.
It is not spread by sharing food, cutlery, cups, hugging, kissing or ordinary household contact. That misconception causes a great deal of unnecessary distress and is worth correcting directly.
What treatment involves now
Modern treatment uses direct-acting antivirals: oral medicines that block specific proteins the virus needs in order to copy itself. They are taken once daily, usually for eight to twelve weeks.
Most people tolerate them well. The side effects reported most often are headache and tiredness, which is a different order of experience from the older interferon-based regimens.
| The interferon era | Direct-acting antivirals | |
|---|---|---|
| How it was taken | Weekly injections plus tablets | Tablets, usually once daily |
| Length of course | Six months to a year | Commonly eight to twelve weeks |
| Side effects | Flu-like illness, mood changes, blood count problems | Usually mild; headache and fatigue most often reported |
| Who could be treated | Many were excluded on other health grounds | Suitable for far more people, including most with cirrhosis |
| Genotype testing | Determined the regimen | Often unnecessary with pan-genotypic regimens |
Week to week during a course
The routine is undemanding. You take the tablets at the same time each day, attend a small number of appointments, and have blood tests to check the liver and confirm the virus is falling.
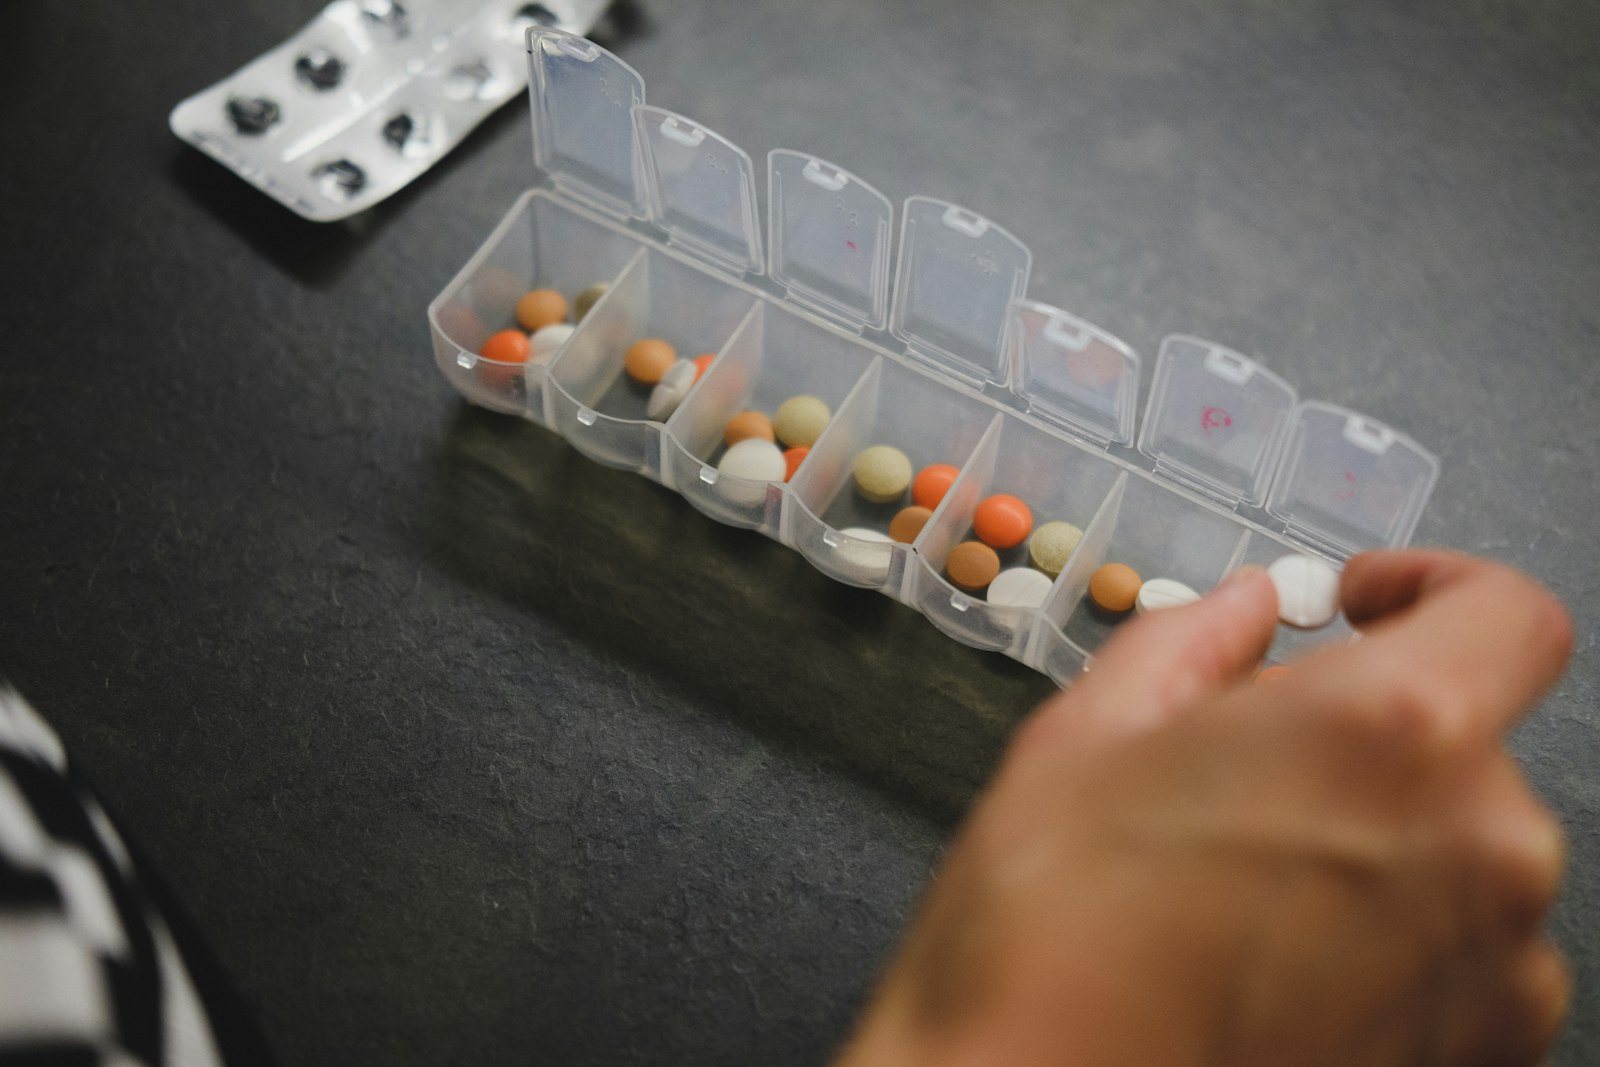
Adherence is the part that matters most. Missed doses are the main avoidable reason a course fails, so a fixed time and a pill organizer are worth setting up on day one.
Tell the prescribing team about every other medicine you take, including supplements and anything bought over the counter. Interactions with these antivirals are real and well documented, and some common medicines need adjusting for the duration.
Appointments during a course are few. Most regimens involve an assessment before starting, a check partway through, and the confirming test afterwards, which is a lighter schedule than many people expect.
Missing a single dose is not a crisis. Take it when you remember unless it is nearly time for the next one, do not double up, and tell the team so the pattern is on record rather than discovered later.
How cure is confirmed
Cure is defined as a sustained virologic response: no detectable virus in the blood twelve weeks after finishing treatment. That blood test is the point at which the infection is considered cleared.

The distinction between finishing treatment and being cured is worth holding onto. The course ending is not the endpoint; the twelve-week test is, and it is important to attend for it.
After treatment
Clearing the virus does not make you immune. Reinfection is possible if you are exposed again, so where risk factors continue, so does the need for periodic testing.
People who had significant liver scarring before treatment continue to need monitoring afterwards, because that scarring does not disappear when the virus does. Those without it generally need no ongoing liver follow-up.

Alcohol is worth discussing honestly with your clinician both during and after treatment, since it compounds liver injury independently of the virus.
Hepatitis C is curable in the great majority of people treated today. If you were told years ago that treatment was not an option for you, that assessment may simply be out of date and is worth revisiting.
Preparing for the first appointment
Bring a complete list of your medicines, including supplements and anything bought over the counter, because interaction checking is a genuine part of choosing a regimen. Bring any previous hepatitis test results you hold.
Expect questions about alcohol, other liver conditions, and previous treatment attempts. These shape the regimen and the length of the course rather than being asked for their own sake.
The patient guide covers what to bring and what to expect administratively, and results and messages are available through the patient portal.
Research and access
This practice takes part in FDA-approved trials of treatments for infectious diseases, especially HIV and hepatitis C, described on our clinical trials page. If a study is ever suggested to you, our guide to questions to ask before joining a clinical trial sets out what to establish first.
Frequently asked questions
Is hepatitis C really curable?
For most people treated with modern direct-acting antivirals, yes. Cure is defined as no detectable virus twelve weeks after finishing the course. Your own likelihood depends on your history and liver condition, which your clinician can discuss.
How long does treatment take?
Commonly eight to twelve weeks of daily tablets. The exact length depends on the regimen chosen, whether you have been treated before, and whether you have cirrhosis.
Will I feel unwell during treatment?
Most people tolerate these medicines well. Headache and tiredness are the side effects most often reported. This is markedly different from the older interferon-based treatments.
Can I be reinfected after being cured?
Yes. Clearing the virus does not confer immunity. If exposure risks continue, periodic retesting is sensible.
Do I still need liver monitoring after cure?
It depends on how much scarring was present beforehand. People with advanced fibrosis or cirrhosis need continued monitoring; those without significant scarring generally do not.
More about the specialty is on the infectious disease physician page, and appointments can be arranged through the contact page.
Sources and further reading: AASLD-IDSA HCV Guidance — Initial treatment of adults.
This article is general health information, not medical advice, and it cannot account for your own history or medications. Discuss your situation with a qualified clinician before acting on anything you read here.