

Sinus infections are one of the commonest reasons people ask for antibiotics, and one of the commonest reasons antibiotics are prescribed when they will not help.
The great majority of sinusitis is viral. It feels every bit as unpleasant as the bacterial kind, which is exactly why the distinction has to be made on pattern rather than on how bad it feels.
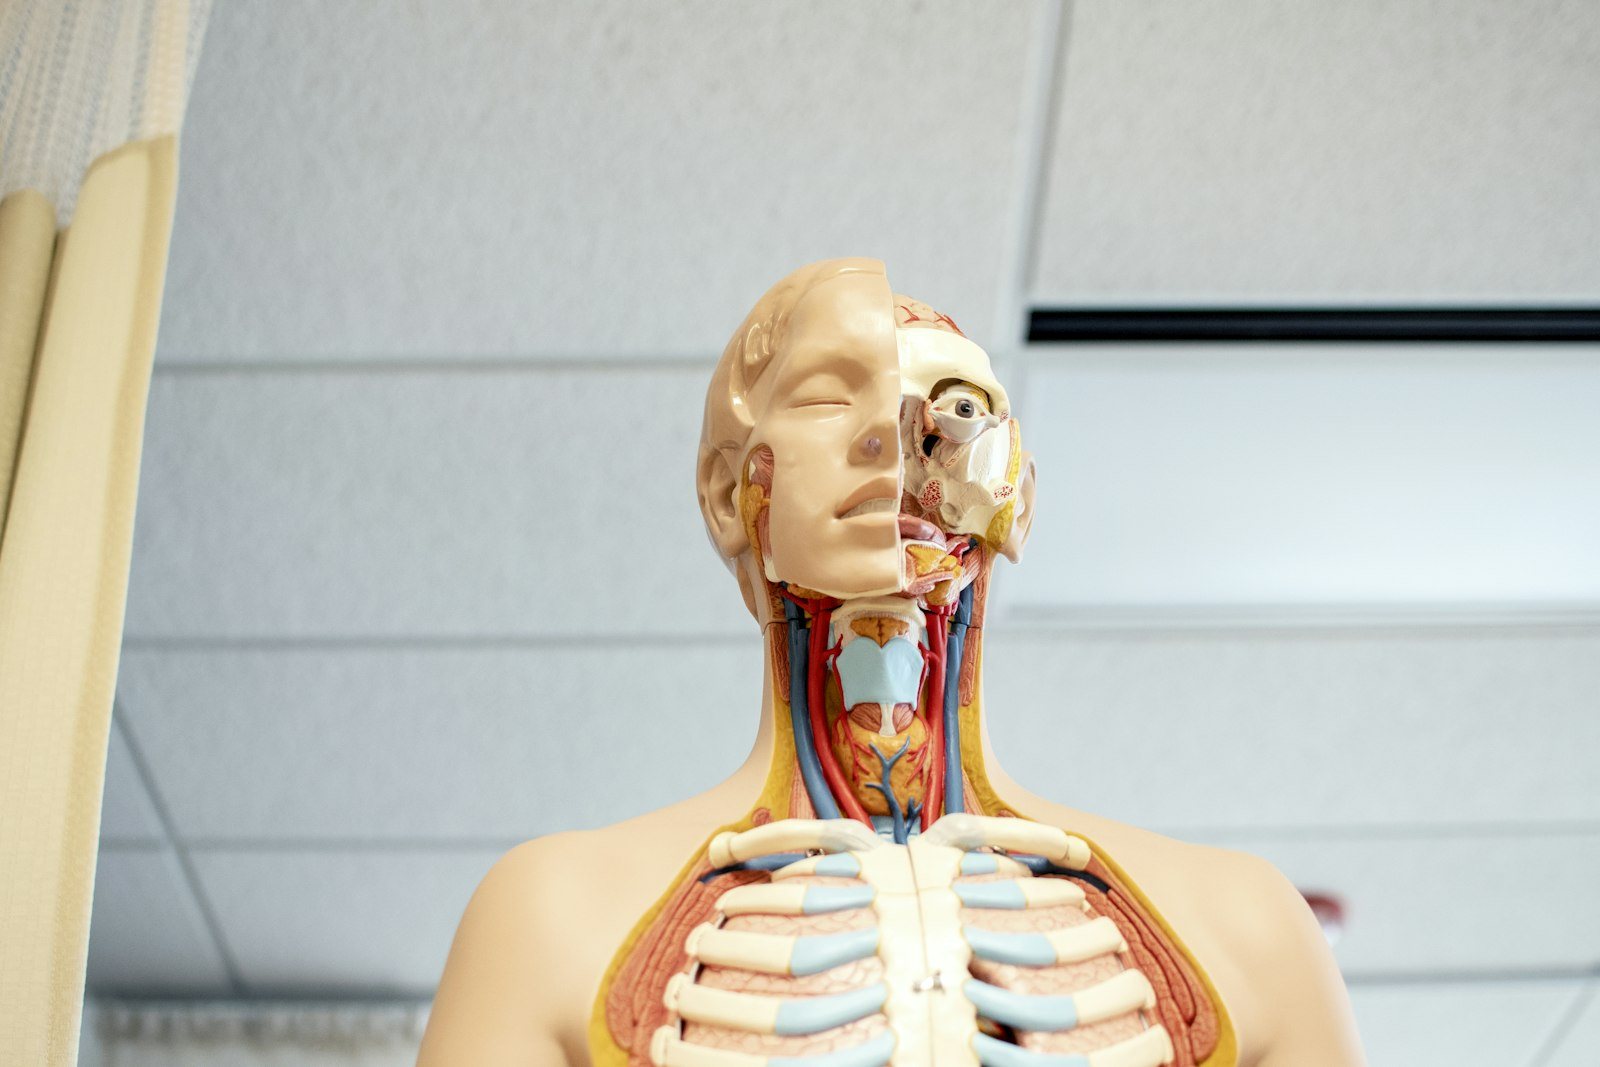
What is actually happening
The sinuses are air-filled spaces in the bones of the face, connected to the nose through narrow openings. Their lining produces mucus that drains out through those openings continuously.
When the lining swells, usually from a viral cold, the openings narrow and drainage stops. Mucus accumulates, pressure builds, and you get the facial pain, congestion and blocked-up feeling that defines sinusitis.
Bacteria only become involved in a minority of cases, when the blocked, fluid-filled space gives them somewhere to multiply. That is a complication of the viral illness rather than how it usually starts.
The usual course, and why patience is the treatment
Viral sinusitis typically peaks around days three to five and improves steadily from there, resolving within seven to ten days.

Thick, discolored mucus is not evidence of bacterial infection. It is what happens when immune cells arrive at the site, and it occurs routinely in ordinary viral colds. This single misconception drives an enormous number of unnecessary prescriptions.
Facial pain that is worse leaning forward, a blocked nose, reduced sense of smell and a feeling of pressure behind the eyes or cheeks are all typical, and none of them distinguishes viral from bacterial on their own.
The three patterns that suggest bacterial infection
Rather than any single symptom, three patterns raise the likelihood enough to consider antibiotics.
| Usually viral | Suggests bacterial | |
|---|---|---|
| Duration | Improving by day seven to ten | Ten days or more with no improvement at all |
| Severity at onset | Moderate, building gradually | Severe from days three to four, with high fever and marked facial pain |
| Pattern | Steady improvement after the peak | Improves, then clearly worsens again — “double worsening” |
| Mucus color | Can be thick and colored | Can be thick and colored |
| Usual treatment | Symptom relief and time | Antibiotics considered |
Notice that mucus color appears in both columns and distinguishes nothing. Duration and trajectory do the work, which is the same logic set out in our article on why antibiotics are not always the answer.
Sinusitis in someone whose immune system is suppressed is assessed differently and earlier, because the usual reassurance about waiting does not apply. The same is true after sinus surgery, and in poorly controlled diabetes.
What genuinely relieves symptoms
None of these shorten the illness, but they make it considerably more bearable, and they work whether the cause is viral or bacterial.

- Saline nasal irrigation or spray, used several times a day
- Steam inhalation, or simply a hot shower
- Acetaminophen or ibuprofen for pain and fever, as directed
- Sleeping with the head elevated on extra pillows
- Plenty of fluids to keep mucus thinner
- Warm compresses over the painful area
Decongestant sprays can help briefly but should not be used for more than about three days, because stopping after longer produces rebound congestion that is worse than the original problem.
Antibiotics are worth taking seriously when they are indicated and worth declining when they are not. Neither position is about toughing it out; both are about matching the treatment to what is actually happening.
When to be seen
Most sinusitis needs no appointment at all. These situations do.

- Symptoms lasting ten days or more with no improvement whatsoever
- Severe symptoms with high fever and marked facial pain from the outset
- Clear improvement followed by a definite worsening
- Four or more episodes in a year
- Symptoms lasting beyond twelve weeks
- You are immunocompromised, or have had sinus surgery
Seek urgent care for swelling or redness around an eye, changes in vision or double vision, severe headache with neck stiffness, confusion, or swelling of the forehead. These suggest spread beyond the sinuses and are emergencies.
One further point about timing. The ten-day threshold assumes no improvement at all across those ten days. Slow but steady improvement at day twelve is still viral sinusitis resolving, and does not need antibiotics.
If antibiotics are prescribed
Take the course as directed and complete it. If there is no improvement after three to five days, go back rather than waiting the course out, because that usually means the organism is not covered by what you were given.
Tell the prescriber about any drug allergy, and about how confident you are in it. As our article on penicillin allergy labels explains, an unexamined label often narrows the options unnecessarily.
What does not help
Several widely used measures have little evidence behind them, and a few make things worse.
- Antihistamines, unless allergy is genuinely the underlying cause
- Decongestant sprays beyond about three days, because of rebound congestion
- Antibiotics for a viral episode, which add side effects without benefit
- Pressing on with strenuous exercise, which tends to prolong the misery
- Repeated courses for recurring episodes without investigating why
The instinct that something must be done is understandable. For most sinusitis the honest answer is that symptom relief and time are the treatment, and that is not the same as being told nothing can be done.
Complete any course you are given even once you feel better, and tell the prescriber if you have had several courses in the past year, because that pattern changes what is appropriate.
Recurrent and chronic sinusitis
Repeated or persistent sinusitis is a different problem from a single episode, and treating each recurrence with another antibiotic course rarely resolves it.

Underlying causes include allergy, structural narrowing, nasal polyps, and occasionally a problem with immune function. Identifying which applies is what changes the pattern, and it usually needs specialist assessment rather than repeat prescriptions.
Frequently asked questions
How do I know if my sinus infection is bacterial?
By pattern rather than by symptoms alone: ten or more days without any improvement, severe symptoms with high fever from the outset, or getting better and then clearly worse again. Mucus color does not distinguish them.
Does green mucus mean I need antibiotics?
No. Colored mucus reflects immune cells arriving at the site and occurs routinely in ordinary viral colds. It is one of the most persistent misconceptions in this area.
How long should a sinus infection last?
Viral sinusitis usually peaks at day three to five and settles within seven to ten days. Beyond ten days with no improvement at all is the point at which reassessment makes sense.
Do nasal rinses actually work?
They do not shorten the illness but they reliably improve symptoms, and they are safe to use several times a day. Use sterile, distilled or previously boiled water rather than water straight from the tap.
When is a sinus infection an emergency?
Swelling or redness around the eye, changes in vision, severe headache with neck stiffness, confusion, or forehead swelling all suggest spread beyond the sinuses and need immediate assessment.
More about the specialty is on the infectious disease physician page, and the contact page explains how to reach the practice.
Sources and further reading: ENThealth (American Academy of Otolaryngology) — Sinusitis.
This article is general health information, not medical advice, and it cannot account for your own history or medications. Discuss your situation with a qualified clinician before acting on anything you read here.