
Going home after an operation means becoming the person who watches the wound. That is a reasonable job to be given, but only if you know what you are watching for.
Some redness, swelling and discomfort around an incision is normal healing. The question is never whether those are present, but whether they are improving or advancing.

What normal healing looks like
In the first few days an incision is usually pink or red at the edges, slightly swollen, warm to the touch and sore. There may be a small amount of clear or lightly blood-stained fluid.
From there it should steadily settle. Redness recedes, swelling reduces, pain decreases, and any drainage stops. The trajectory is downward, day by day.
Bruising, itching as it heals, and a firm ridge along the incision are all normal and often alarming to people who were not told to expect them.
The timeline that matters
Most surgical site infections appear within thirty days of an operation, and typically in the first week or two. Where an implant was placed, the window extends considerably longer.
| When | Normal | Concerning |
|---|---|---|
| Days one to three | Redness at the edges, swelling, soreness, clear fluid | Spreading redness, fever, rapidly increasing pain |
| Days four to seven | Redness fading, pain decreasing, drainage stopping | New or increasing redness, warmth, pus, or a returning fever |
| Week two onward | Edges closed, firm ridge forming, itching | Wound opening, new drainage, foul odor, worsening pain |
| Beyond thirty days | Scar maturing and fading | Late pain or swelling near an implant, needing assessment |
Infections around implanted material behave differently and can appear months or years later, which is covered in our article on bone and joint infections.
Where an operation involved a joint replacement, mesh, a graft or any implanted material, the threshold for reporting is lower and the relevant window is far longer than thirty days.
The signs to report
- Redness spreading outward rather than receding, especially in red streaks
- Increasing rather than decreasing pain
- Fever, chills, or feeling generally unwell
- Cloudy, yellow, green or thick discharge, or any pus
- A bad smell from the wound
- The wound edges separating, or the wound opening
- New swelling, hardness or warmth around the incision
The most useful single technique is the same one used for cellulitis: draw a line around the edge of the redness with a pen and note the time. Comparing against that line removes the guesswork.
Call the surgical team the same day for fever, pus, spreading redness or rapidly worsening pain. Seek emergency care if the wound opens widely, if you feel confused or very unwell, or if you have the warning signs of sepsis.
Keep the surgical team informed rather than routing everything through a general practice or an urgent care center. They know what was done, what was implanted and what the wound looked like when you left, and none of that is obvious from the outside.
Most teams would far rather field a call that turns out to be nothing than see a problem three days later. Say so directly if you feel you are bothering them; you are not.
Caring for the incision

- Wash your hands thoroughly before and after touching the wound or dressing
- Follow the specific instructions you were given about showering and getting it wet
- Keep dressings clean and dry, and change them as instructed
- Do not apply creams, ointments or antiseptics unless you were told to
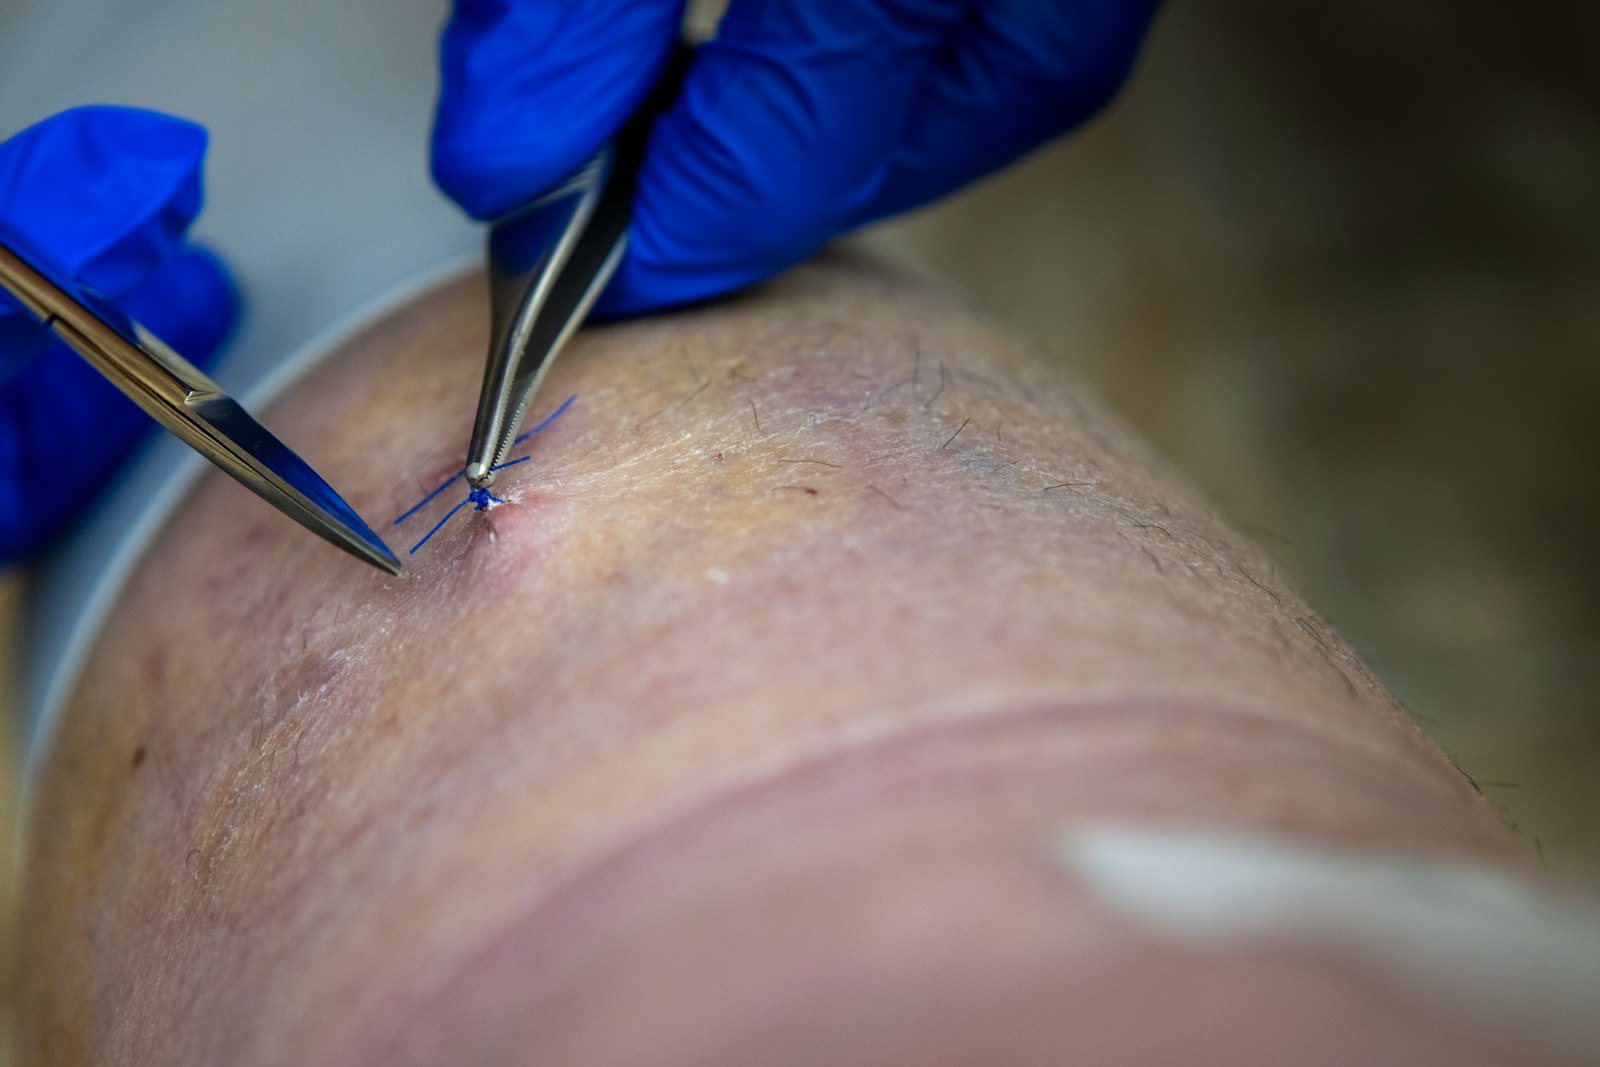
- Do not pick at scabs, and do not remove sutures or staples yourself
- Wear loose clothing that does not rub against the site
Instructions vary genuinely between operations and between surgeons. Where what you were told differs from general advice, follow what you were told, and ring the team if you cannot remember.
Pain, and what it tells you
Post-operative pain should follow a downward curve. Day three should be better than day two, and week two better than week one, even if progress is uneven from hour to hour.
Pain that increases after having settled is one of the more reliable early signs that something has changed, and it often precedes visible redness or discharge by a day or more.
It is worth reporting for that reason, even when the wound itself looks unremarkable. “It was getting better and now it is worse” is a sentence surgical teams take seriously.
Not every wound problem is infection. Fluid collections, small areas of separation and stitch reactions all occur without infection and are managed differently, which is another reason to be assessed rather than to self-diagnose.
What raises the risk
- Diabetes, particularly with blood glucose that is not well controlled
- Smoking, which measurably impairs wound healing
- Obesity, and poor nutrition
- A long or emergency operation, or one on the abdomen or bowel
- A suppressed immune system, or treatment with steroids
- Existing infection elsewhere in the body at the time of surgery
Several of these are modifiable, which is why pre-operative preparation matters. Stopping smoking and improving glucose control in the weeks before surgery both reduce the risk measurably.
Take a photograph of the incision each day in similar light. Comparing images over three days is far more reliable than comparing today against your memory of yesterday, and it gives the team something concrete if you do need to call.
If an infection develops
Most surgical site infections are superficial and are treated with antibiotics, often with the wound opened and cleaned. Deeper infections, or those involving implanted material, need more.

Treatment may involve drainage, removal of infected tissue, a longer antibiotic course, and sometimes intravenous antibiotics continued at home through an office infusion center.
Where a wound will not close afterwards, that becomes a separate problem with its own causes, set out in our article on why some wounds do not heal, and may need specialist wound care.
Frequently asked questions
How much redness is normal after surgery?
Some redness at the incision edges is normal in the first days. What matters is direction: it should recede rather than expand. Redness spreading outward, especially with fever or increasing pain, should be reported the same day.
When do surgical site infections usually appear?
Most within thirty days of the operation, commonly in the first week or two. Where an implant was placed the window is much longer, and late pain or swelling near it should be assessed.
Can I shower with my incision?
Usually yes after a specified point, but instructions differ by operation and surgeon. Follow what you were told, and ring the team rather than guessing if you cannot remember.
Is clear fluid from the wound normal?
A small amount of clear or lightly blood-stained fluid can be normal early on. Cloudy, yellow, green or thick discharge, or any pus, is not, and should be reported.
Should I put antiseptic cream on it?
Not unless you were specifically told to. Many creams and antiseptics interfere with healing, and applying them can obscure the appearance the team needs to assess.
More about the specialty is on the infectious disease physician page, and the contact page explains how to reach the practice.
Sources and further reading: American College of Surgeons — Recovering from surgery.
This article is general health information, not medical advice, and it cannot account for your own history or medications. Discuss your situation with a qualified clinician before acting on anything you read here.